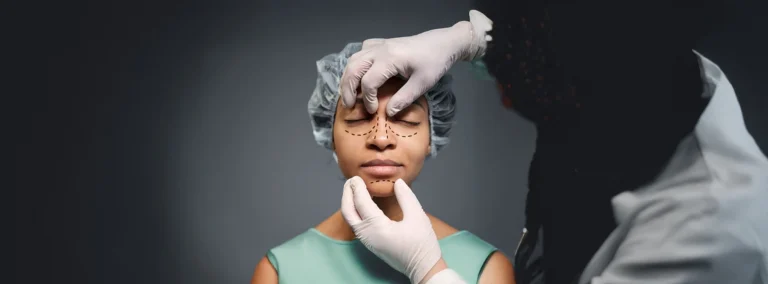
Rhinoplasty is surgery that reshapes the nose and, when the septum is involved, improves breathing. It is done under general anaesthesia, the splint comes off after about a week, most swelling settles within six months and the final result is seen at 12 to 18 months.
- Rhinoplasty can change the bridge, tip, nostrils and alignment of the nose, and can correct breathing problems in the same operation.
- Suitable candidates are healthy adults with complete facial growth, a clear concern and realistic expectations.
- Open and closed techniques are chosen according to what needs to change, not as a matter of preference.
- The splint is removed after about a week; most swelling settles in three to six months and the final shape shows at 12 to 18 months.
- Patients travelling from abroad usually plan a stay of seven to ten days, until the splint is removed and the nose is checked.
Rhinoplasty is surgery that changes the shape of the nose, and when needed, the way air moves through it. It can lower a hump on the bridge, refine or lift the tip, narrow wide nostrils, straighten a nose that has drifted after an injury and bring the nose into proportion with the rest of the face. When the internal partition of the nose, the septum, is bent and blocks breathing, it is usually corrected in the same operation.
A well-planned rhinoplasty rarely aims for a “new” nose. The goal is a nose that suits the face it sits on: it should look as if it has always been there. This page explains who the operation suits, what it can and cannot change, how it is done, what recovery looks like week by week, the risks, and what patients travelling from abroad need to plan for.
Who Is a Good Candidate for Rhinoplasty?
Rhinoplasty suits adults in good general health whose facial growth is complete, who have a specific concern about the shape or function of their nose and who have realistic expectations about what surgery can achieve. Facial growth is usually complete by the mid-to-late teens; surgery before that point is reserved for breathing problems or injuries that cannot wait.
The people who tend to be most satisfied share a few traits:
- A clear, describable concern. “The hump is visible in profile” or “the tip droops when I smile” can be planned for; “I just don’t like my face” usually cannot be solved with nasal surgery alone.
- Stable health. Uncontrolled blood pressure, bleeding disorders and certain medications raise the risk of bleeding and need to be dealt with first.
- Non-smokers, or people willing to stop. Smoking reduces blood flow to the skin and cartilage and slows healing.
- Patience with swelling. The nose changes gradually over a year or more, especially at the tip and in thicker skin.
Whether the operation is worth it for a particular person depends on how much the nose bothers them, whether breathing is part of the problem and how much change is realistic. These questions are explored in detail in is rhinoplasty worth it?
What Rhinoplasty Can Change
Every nose is made of the same building blocks: nasal bones at the top, cartilage in the middle and at the tip, the septum in the centre and a covering of skin whose thickness varies from person to person. Rhinoplasty works on these structures to change specific features.
The bridge and the dorsal hump
A hump on the bridge is made of bone above and cartilage below. It can be lowered by rasping or trimming, and the nasal bones are then brought closer together so the bridge does not look flat and wide from the front. When the hump is small and the rest of the nose is in proportion, a more limited operation may be enough; this is covered on the nose filing page. For noses that are large overall rather than humped, see nose reduction surgery.
The tip
The tip is shaped by the lower lateral cartilages. A drooping, wide, boxy or bulbous tip can be refined by reshaping these cartilages and supporting them with small cartilage grafts, so the tip keeps its position as the nose heals. When only the tip needs work, a tip-focused operation may be planned; see nasal tip aesthetics. Thick skin limits how sharply a tip can be defined, which is discussed in bulbous nose rhinoplasty.
The nostrils
Wide or flaring nostrils can be narrowed by removing a small wedge of skin where the nostril meets the cheek. This is often combined with rhinoplasty but can be done on its own; see alarplasty surgery.
A crooked nose
A nose that has moved off centre, usually after an old injury, needs the bones, the middle vault and the septum to be realigned together. Some asymmetry is normal in every face, so the aim is a nose that reads as straight rather than one that is perfectly symmetrical. More on this in crooked nose.
The profile as a whole
A nose can look larger than it is when the chin is set back. In these cases a small chin implant placed at the same time can balance the profile with a more modest change to the nose; see rhinoplasty and chin implant together.
What rhinoplasty cannot do is change the underlying character of a face, promise perfect symmetry or make thick skin behave like thin skin. A good plan respects these limits.
Breathing, the Septum and Functional Surgery
Many people who come for a cosmetic change also have some difficulty breathing through one or both sides of the nose. The usual causes are a deviated septum, enlarged turbinates (the ridges on the side walls of the nose) or a weak middle vault that collapses inwards on breathing in.
When these problems are present, they are assessed before surgery and corrected in the same operation. Combining the two is known as septorhinoplasty, and it allows the nose to look and work better without a second anaesthetic. The technique, recovery and limits are explained in septorhinoplasty, and surgery aimed mainly at breathing is described on the functional nose surgery page.
Changing the outside of the nose should never come at the expense of breathing. Making a nose much smaller can narrow the airway, which is one reason modest, structure-preserving changes are usually preferred.
Open or Closed Rhinoplasty
There are two main ways to reach the structures of the nose:
- Closed rhinoplasty: all incisions are made inside the nostrils, so there is no visible scar. It suits noses that need changes mainly to the bridge or limited work on the tip, and swelling often settles a little faster.
- Open rhinoplasty: a small incision across the columella, the strip of skin between the nostrils, allows the skin to be lifted and the cartilages to be seen directly. It is preferred for complex tips, crooked noses, extensive grafting and most revision operations. The scar is short and usually fades to a fine line that is hard to see at conversational distance.
Neither approach is better in general; the choice depends on what needs to be changed. Within either approach, surgeons may use powered or ultrasonic instruments to reshape bone more precisely, and preservation techniques that lower the bridge without removing its natural surface. These options are discussed at the consultation and chosen to fit the nose rather than the other way round.
The Consultation and Planning
Planning starts with a careful look at the whole face, not just the nose. The surgeon examines the nose from the front, side and below, checks the skin thickness, feels the cartilage support at the tip and looks inside the nose to assess the septum and turbinates. Standardised photographs are taken so changes can be discussed precisely.

The consultation is also where expectations are matched to anatomy. It helps to bring a short list of what bothers you most, in order of priority, and any history of nasal injuries, previous surgery, allergies or sinus problems. Some patients find it useful to bring photographs of noses they like, as long as they accept that the result has to fit their own face, skin and bone structure.
For patients who live abroad, a first assessment can be made from photographs and a video call, with the in-person examination taking place a day or two before surgery.
How the Operation Is Done
Rhinoplasty is performed under general anaesthesia in a hospital operating theatre. Depending on how much work is needed, the operation usually takes between one and a half and three hours; septorhinoplasty and revision surgery take longer.
After the incisions are made, the bones and cartilages are reshaped according to the plan. Cartilage for grafts is usually taken from the septum; when more is needed, it can be taken from the ear or, in revision cases, a rib. Once the shape is set, the incisions are closed with fine stitches, an external splint is placed on the bridge, and soft silicone splints may be placed inside the nose to support the septum. Most patients stay one night in hospital.
Rhinoplasty Recovery: What to Expect Week by Week
Recovery follows a fairly predictable pattern, although the speed varies with skin thickness, the extent of surgery and whether the bones were moved.
- Days 1–3: The nose feels blocked and there is swelling and bruising around the eyes, which usually peaks on the second or third day. Sleeping with the head raised and using cold compresses on the cheeks help.
- Days 5–8: The external splint and any internal splints are removed. The nose looks swollen and may be taped for a while longer. What patients see on this day, and why it is not the final shape, is explained in rhinoplasty splint removal.
- Weeks 2–3: Most bruising has faded and many people return to desk work and social life, although the nose still looks fuller than it will eventually be.
- Weeks 4–6: Breathing feels clearer and gentle exercise can resume. Heavy glasses resting on the bridge are usually avoided for several weeks; see glasses after rhinoplasty.
- Months 3–6: Most of the swelling has gone and the new shape is clearly visible.
- Months 12–18: The last of the swelling, mainly at the tip and in thick skin, settles and the final result can be judged.
Day-by-day details on sleep, breathing, nasal care and the return to activities are covered in rhinoplasty recovery, and the long tail of tip swelling in rhinoplasty swelling. Contact sports and activities that risk a blow to the nose are usually postponed for around two to three months.
Risks and How They Are Reduced
Like any operation, rhinoplasty carries risks. Most are uncommon and many are temporary, but they should be understood before deciding.
- Bleeding: Some oozing in the first day or two is expected. Significant bleeding is rare and is less likely when blood pressure is controlled and blood-thinning medicines and supplements are stopped in advance on medical advice.
- Infection: Uncommon, and usually treated with antibiotics.
- Breathing difficulty: Temporary blockage is normal while swelling lasts. Lasting obstruction can occur if the airway is narrowed, which is why structural support is preserved or rebuilt.
- Numbness and changes in skin sensation: The tip may feel numb for several months.
- Irregularities and asymmetry: Small irregularities can become visible as swelling settles, especially in thin skin.
- Need for revision: A minority of patients, often quoted at around one in ten, choose a further operation to fine-tune the result. Revision is usually not considered until at least a year after the first operation; see revision rhinoplasty and the revision nose surgery page.
Careful planning, a realistic goal, conservative changes and close follow-up during healing are the main ways these risks are kept low.
Travelling Abroad for Rhinoplasty
Patients who travel for rhinoplasty need to plan their stay around the healing timeline rather than the operation date. A typical plan is an in-person assessment one or two days before surgery, the operation with an overnight hospital stay, and then remaining nearby until the splint is removed and the nose has been checked, usually seven to ten days in total.
Flying is generally possible once the splint is off and there is no bleeding, although the nose may feel congested during descent. Swelling at the time of flying home is normal and will continue to settle over the following months, so it helps to arrange follow-up by photograph or video call and to know who to contact if a concern arises after returning. The practical side of planning, including timing, aftercare at home and safety points, is set out in rhinoplasty in Turkey; for second operations see revision rhinoplasty in Turkey.
Non-Surgical Alternatives
Injectable fillers can disguise a small hump or lift the tip slightly by adding volume in selected areas. They do not make the nose smaller, cannot improve breathing and wear off over months. Filler in the nose also carries rare but serious vascular risks, so it needs an experienced injector. For a balanced view of what it can and cannot do, see non-surgical nose job.
Rhinoplasty Frequently Asked Questions
How long do rhinoplasty results last?
The changes made to bone and cartilage are long-lasting. The nose continues to age along with the rest of the face, so the skin and tip may soften slightly over decades, but the overall shape created by surgery remains.
Is rhinoplasty different for men?
Yes. Men usually have thicker skin and a stronger, straighter bridge is generally preferred, with less upward rotation of the tip. Over-refining a male nose can make it look out of place on the face. See male rhinoplasty.
Will the tip drop after surgery?
Some settling of the tip is normal as swelling resolves. Modern techniques support the tip with cartilage grafts and stitches to reduce unwanted drooping over time.
Can I have rhinoplasty if I have sinus problems or allergies?
Usually yes, but active sinus infection or poorly controlled allergies should be treated first. Long-standing sinus disease may need assessment by an ear, nose and throat specialist before surgery.
Is there a best time of year for rhinoplasty?
There is no medical advantage to any season. Some patients prefer cooler months because sun exposure and swimming are limited for several weeks after surgery, and a hat and sun protection are needed in summer.
Will rhinoplasty change my voice?
Most people notice no lasting change. The voice can sound nasal while the nose is congested in the first weeks, and a small change in resonance is occasionally noticed once breathing improves.
When will I see the final result?
The nose looks noticeably better within a few weeks, most swelling has gone by three to six months, and the final shape is usually visible at 12 to 18 months, later in thick skin.
References
- Rhinoplasty — American Society of Plastic Surgeons
- Rhinoplasty — British Association of Aesthetic Plastic Surgeons
- Rhinoplasty (Nose Job): Surgery and Recovery — Cleveland Clinic
Professor Şükrü Yazar, Consultant Plastic, Reconstructive and Aesthetic Surgeon, sees patients for rhinoplasty consultations at his practice in Nişantaşı, Istanbul, where the plan is tailored to each nose and face.
The information here is for guidance only and does not replace examination, diagnosis or treatment.